Keywords
Speech and language therapy, waiting times, neurodevelopmental assessment, ADHD, Autism, early identification, community paediatric services

Speech and language therapy, waiting times, neurodevelopmental assessment, ADHD, Autism, early identification, community paediatric services
 How to cite: Cantrell A, Lagojda L, Pulsford E and Simpson E. A mapping review of sustainable transformations to reduce waiting time for speech and language therapy (SALT) or neurodevelopmental assessment within a community paediatrics service [version 1; peer review: awaiting peer review]. NIHR Open Res 2026, 6:147 (https://doi.org/10.3310/nihropenres.14340.1)
First published: 12 Sep 2026, 6:147 (https://doi.org/10.3310/nihropenres.14340.1)
Latest published: 12 Sep 2026, 6:147 (https://doi.org/10.3310/nihropenres.14340.1)
Community paediatric services are imperative in supporting the development and well-being of children and young people. However, many of these services face significant operational pressure, particularly concerning waiting lists. There are high numbers of waits for Speech and Language Therapy (SALT) services and neurodevelopmental assessments within community services, and waiting lists are growing. Written evidence from the Royal College of Speech and Language Therapists to the House of Lords reported that in February 2023, there were 65,871 children on the waiting list for SALT services, 20,048 of whom had been waiting for up to a year.1 A report on waiting lists for Attention Deficit Hyperactivity Disorder ADHD assessment by ADHD UK found significant variation for children from five weeks to five years and that most NHS commissioning services actually do not know the exact waiting times for their services.2 Recent NHS England statistics from April 2024 to March 2025 reported that in March 2025, there were 224,382 patients with an open referral for suspected autism, and 89.9% of these patients had been open for at least 13 weeks.3
These waiting times starkly contrast with established clinical recommendations. The NICE guideline on autism spectrum disorder in under 19 s explicitly recommends starting a diagnostic assessment within 3 months (approximately 13 weeks) of referral to the autism team (1.5.1).4 Waiting significantly longer than clinically appropriate is much more than an inconvenience; it can delay timely access to support, potentially leading to increased case complexity and impeding children from achieving vital educational and developmental milestones.5 The consequences ripple outwards, impacting downstream service utiliation and wider societal outcomes, such as future employment prospects and interactions with the justice system. Delays also exert considerable pressure on families, carers, and educational settings, challenges illustrated in the Children’s Commissioner’s report, and these experiences resonate with the need identified in guidance to support families and carers and ensure that services promote quality of life, wellbeing, choice, and control.6
Current waiting lists are lengthening3,7 due to a sustained increase in the demand for neurodevelopmental assessments, potentially reflecting better recognition8 but occurring without a corresponding expansion in community capacity or resources. This aligns with national efforts, such as the NHS England framework designed to improve outcomes in all-age autism assessment pathways.9 This framework sets out the principles intended to underpin pathways that work for everyone, irrespective of background, to improve the quality of information and support, increase efficiency, reduce uncertainty during the process, enhance user satisfaction and confidence, and address known health inequalities. This situation necessitates a critical review of current practices and the exploration of novel approaches.
This mapping review was conducted for NHS England as part of the National Institute for Health Research Health Services & Delivery Research Sheffield Evidence Synthesis Centre contract, and the protocol is on Open Science Framework (https://osf.io/ckr6d/). During the project, there was regular consultation with the stakeholders inat NHS England, ensuring that the review was informed by their views and experiences. This review aims to identify innovative solutions, both those requiring and not requiring additional funding and those achievable through service redesign that reduce waiting times and improve the quality of care, experiences, and outcomes for children, young people, and their families accessing these services. Guided by principles of person-centred8 and neurodiversity-affirming practice,10 this review will explore innovative strategies including, but not limited to, 1) efficient pathway management; 2) effective use of digital tools; 3) earlier identification of needs; 4) and the provision of meaningful support for those waiting for assessment4,6,10 - ultimately seeking models to enable timely and effective community-based care.8
The aim was to identify and map examples of sustainable transformations or initiatives within speech and language therapy and neurodevelopmental assessment service provision under a community paediatrics service in the UK, both with and without additional funding, to provide guidance for commissioners and providers. Additionally, for SALT services research from countries with similar healthcare systems (Australia and Canada) were included. This study does not involve human participants.
What pathways and transformational approaches have been used to:
1. Reduce waiting times.
2. Support children and young people awaiting assessment to prevent deterioration and wider impact of unmet needs.
3. Improve earlier identification of needs, including in early years and educational settings.
This review focuses on the following community services for children and young people aged 0–19:
• Speech and Language Therapy (SALT).
• Neurodevelopmental Assessments delivered under a community paediatrics service, covering autism or ADHD service, or the development of a single neurodevelopmental pathway.
This systematic mapping review closely adheres to published methods for mapping reviews.11,12
The searches for evidence comprised a focused database search for recently published research and an extensive search of relevant websites for examples of good practice. The MEDLINE, PsycINFO, HMIC, CINAHL, and ASSIA databases were searched. The search covered the period 2020–2025 and was restricted to items in English only. The search cut-off date was determined by the need to optimise the relevance to the current context and ways of working. Supplementary searching of the websites of key UK research organisations and professional associations was also conducted to identify reports about service transformation or initiatives within community services. Full details of the search process, including search strategies for all databases and websites, are provided at https://doi.org/10.15131/shef.data.31652083.
Studies included in the mapping review studied children and young people aged 0–19 years in the UK or similar health care systems. Included interventions were approaches to reduce waiting times, measures to support children and young people and their families during waiting periods, and methods to support early identification of need. Published literature (articles, reports, and guidelines) and examples of good practice/initiatives written in English were included from 2020–2025.
The search results were managed using Endnote 21 (https://endnote.co.uk/) and imported into Rayyan (https://new.rayyan.ai/) for study selection. This was an evidence synthesis project; thus, no confidential patient information was used. The titles and abstracts of all references from the database search were screened in Rayyan using the eligibility criteria to determine inclusion. Screening decisions were compared and discussed until consensus was reached. Articles meeting the inclusion criteria or items with insufficient detail on content were reviewed in the full-text. Additionally, all items retrieved by the grey literature search were reviewed at full-text due to the nature of the items that were mainly missing an abstract. Again, there was an initial independent screening of a sample of full-text to ensure consensus, then the remaining references were screened by one reviewer with any unclear references discussed, and there was a 10% check of all screening decisions.
The data extraction form, constructed in Google Sheets, was piloted, and amendments made where necessary. Includes were then data extracted by one reviewer. We extracted data relating to study population (e.g., age, ethnicity, socioeconomic status), setting (e.g., study location, service setting), intervention (e.g., approach, digital tools, region/commissioning board), and outcomes (e.g., implementation-enabling factors, implementation barriers, time on waiting list). A sample of data extractions (approximately 20%) were assessed for consistency across multiple reviewers.
Aspects of successful pathways/service models were identified and organised in a narrative discussion with information about the quality and quantity of the evidence. Data was mapped using Excel (Microsoft® Excel® for Microsoft 365 MSO (Version 2508 Build 16.0.19127.20622) 64-bit).
Stakeholder involvement
During the review process, we regularly consulted with stakeholders at NHS England and the National Institute for Health and Care Research. This ensured that the review was informed by the views and experiences of stakeholders.
Patient and Public Involvement
Prior to commissioning the review, the Transforming Children and Young People’s Community Services programme has held sessions with parents and carers to learn about their experiences, concerns, and recommendations. During the review process a standing PPI group commented on the plain language summary for the report submitted to NHS England and included in this publication. Following submission of our report the Transforming Children and Young People’s Community Services programme could arrange additional sessions to provide feedback on the research findings.
The PRISMA flow diagram produced in Rayyan ( Figure 1 PRISMA flow diagram) summarises the literature search and article screening (sifting process).
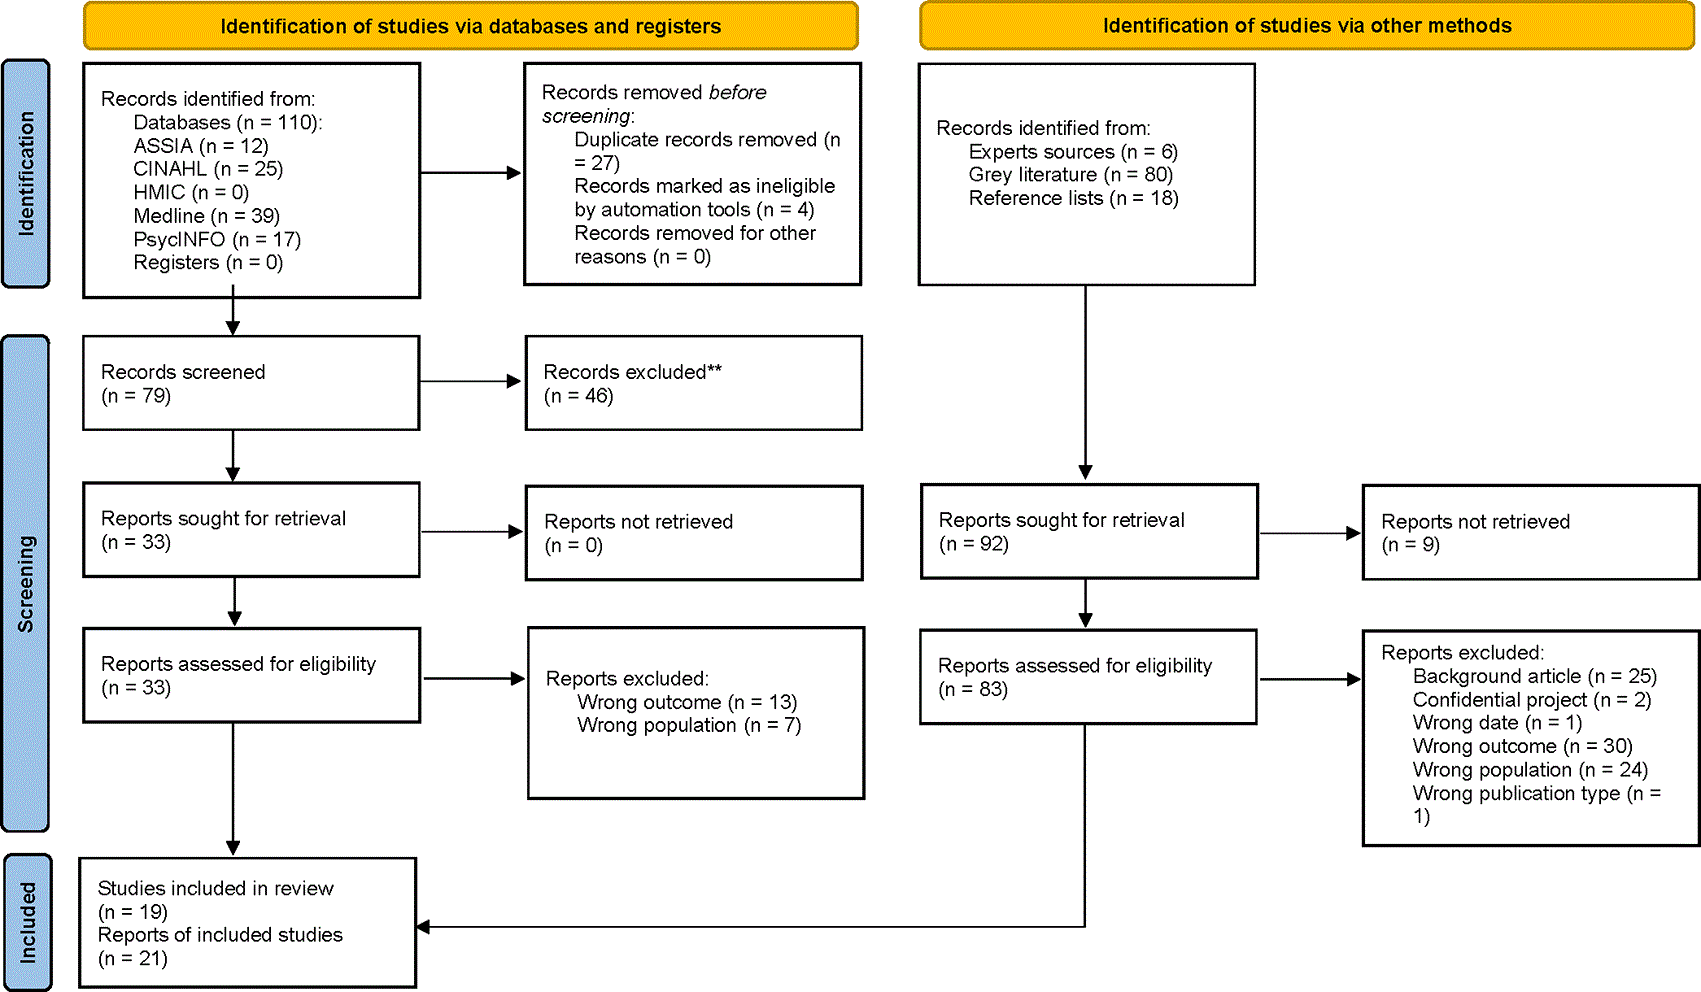
The mapping review includes 19 studies, comprising 21 items of evidence. The majority of the included studies (13) were from the UK, a further five studies were from Australia, and one study was from Canada. Study characteristics are provided in Table 1. Additional information on the interventions was extracted using TIDERLite and is provided in the Supplementary Material at https://doi.org/10.15131/shef.data.31652083
| Reference | Study design | Setting | Study population | Age of children | Place in pathway |
|---|---|---|---|---|---|
| McLeod, S. et al. 202013 | Randomised controlled trial (n = 110) | Two community Health Centres, New South Wales, Australia | Children referred to speech-language pathology waiting lists | 3–6 years | Waiting for SALT |
| Autistica, 202114 | Report of case studies of four services starting to diagnose multiple conditions in a single assessment process. | Integrated Neurodevelopmental Service - integrating paediatric service and Child and Adolescent Mental Health Services (CAMHS), Peterborough, UK (only case study with results) | Children referred for diagnosis of various neurodevelopmental conditions | Pre-school through to school-age children | Entire pathway |
| McGill, N. et al 202115 | Randomised controlled trial (n = 42) | Community health centre, New South Wales, Australia | Children with speech/language difficulties | Preschool aged children, 3–6 years | Waiting for SALT |
| National Autism Implementation Team (NAIT), Scotland Neurodevelopmental pathway (Maciver, D. et al. 2025 and Rutherford, M. 2020)16,17 | Rutherford - Consultation and consensus process, for development of pathway Maciver - Cross-sectional retrospective case note review | National Autism Implementation Team (NAIT), Scotland, UK | Pathway for neurodevelopmental assessment and diagnosis | 0–18 years | Entire pathway |
| Early Language in Victoria Study (ELVS) (Eadie, P. et al. 2022)18 | Prospective cohort (n = 1208) | Community sample of infants from 6 government areas in Melbourne, Victoria, Australia | Children in general population, identifying those with need for SALT | Infants were recruited aged 7.5 to 10 months, annual data collection until 7 years old. | Pre-screening |
| Evans, K. et al. 202219 | Qualitative online survey (professionals & users/carers) | Neurodevelopmental services in Australia (Practice settings include hospital, community-based clinic, school, private practice and other.) | Health professionals (Occupational Therapists, Paediatricians, Physiotherapists, Psychologists, SALT) & service users/carers (mostly parents) for various neurodevelopmental disorders | Up to 18 years (median service user aged 4 years) | Diagnosis Pathway |
| Spain, D. et al. 202220 | Qualitative interview study (health professionals) | Autism services, neurodevelopmental or mental health, mostly NHS some private healthcare, services across England | Health professionals (37% child services, 14% lifespan) | Professionals worked with children, adults, or across lifespan | Diagnostic Assessment |
| County Durham and Darlington Needs Led Neurodevelopmental Pathway (County Durham Care Partnership n.d. and Wilson, A. and Gunnn, S. 2023)21 22 | County Durham - Case study Wilson - Mixed-methods study | County Durham Care Partnership, County Durham and Darlington, UK | Children referred for diagnosis of multiple neurodevelopmental conditions | Children and young people | Entire pathway |
| Gascoigne, M. et al. 202323 | Case study, quality improvement | NHS Trust, Worcestershire, Lancashire, UK (2 case studies) | Children and families requiring SALT | Pre-school and school age | Pre-referral and waiting list |
| Albon, H. et al. 202424 | Prospective cohort/pilot intervention (n = 9) | Kingston & Richmond CAMHS SPA, London, UK | Parents of children awaiting autism or ADHD assessment (n = 9) | 6–9 years | Pre–assessment support |
| Central and North West London NHS Foundation Trust. 202425 | Quality Improvement Project | Community Paediatric Service, Milton Keynes, UK | Children and Young Adults | 11–18-year-olds | Entire pathway |
| Hannant, P. 202426 | Case study (n = 3 cases) | Education and Healthcare, UK | Children with suspected neurodevelopmental disability | 3 children, aged 6–8 years | Entire pathway |
| Harding, K. et al. 202427 | Implementation trial Pre-post prospective cohort (n = 2564 of whom 1187 (46%) speech pathology) | Paediatric community health services, Melbourne, Australia | Children presenting to paediatric service, includes speech or language difficulties | Majority preschool age | Waiting for SALT (or other paediatric therapy services including occupational therapy and other allied health services) |
| Hertfordshire Community NHS Trust. 202428 | Case study, quality improvement | Community NHS Trust, Hertfordshire, UK | Children and young people requiring integrated therapy services including SALT, physiotherapy and occupational therapy | 0–25 years | Pre-referral and waiting list |
| Maier, A. et al. 202429 | Implementation trial, (n = 95) | Clinical preschool speech and language program setting, Ontario, Canada | Young children late to talk | Parents of children identified as late talkers between 18–30 months | Waiting for SALT |
| National Institute for Health and Care Excellence. 202430 | Guidance | NHS ADHD diagnosis | People with suspected autism | Any age | Digital tools for diagnostic assessment |
| Parr, J. et al. 202431 | Survey | Childhood Autism Assessment Services in UK (NHS services - integrated (8%), CAMHS (36%), paediatric services 56%) | Clinicians from UK childhood autism diagnostic assessment services | 1–18 years (specific age range seen depended on service) | Diagnostic assessment |
| Smith-Young, J. et al. 202532 | Systematic review of qualitative studies | International (13 countries incl. UK) | Parents/carers of children referred for/diagnosed with autism | Children 1.5–18 years | Entire pathway |
| Cambridgeshire and Peterborough NHS Foundation Trust. n.d.33 | QI/Service change (“PDSA”), Before-after study | Cambridgeshire Lifespan Autism Spectrum Services, Cambridgeshire and Peterborough, UK | Referrals to CLASS (Cambridgeshire Lifespan Autism Spectrum Service) | Not reported | Screening/assessment |
Thirteen of the included studies mapped to the objective of reducing waiting times, see Table 2. A study implementing the Specific Timely Appointments for Triage (STAT) in paediatric services (including SALT) reported a significant reduction in waiting times through structured appointment management, with waiting times reduced by 33%.27 The model starts by reducing the backlog of patients on the waiting list, and involves scheduling a specified number of screening appointments each week. A “hub and spoke” approach was used to train champions of STAT from each who then shared with their centres.27
| Reference | Review objective 1: reduce waiting times |
|---|---|
| NAIT (Maciver, D. et al 2025 and Rutherford, M. 2020)16,17 | Rutherford - pathway developed includes quality standards for wait times and recommends that local pathways should include time standards. Maciver - Quality standards:
Association between adherence to best-practice quality standards and shorter waits for children/adolescents (β = 0.27, p = 0.002). |
| Autistica, 20214 | Peterborough - significant reduction in waiting times since 2015. Pre-intervention time on waiting list could be over a year. Post-intervention waiting times were 7–12 weeks. “Referral-to-diagnosis rate risen from 40% to 73%” Referrals to the service have increased to 50–60 per month but no baseline data provided. |
| Evans, K. et al. 202219 | Facilitators: professional awareness/training, active listening, clear info (checklists), consistent/monitored process, minimise “wait and see”, more funding/staff, local/culturally appropriate providers, holistic assessment, cross-discipline/inter-agency communication (indirectly). |
| Spain, D. et al. 202220 | Facilitators: convenience, flexibility, encouraged innovation, accessibility (fewer missed appts, fill cancellations), reduced travel/room costs, wider staff recruitment (indirectly). |
| (County Durham Care Partnership n.d. and Wilson, A. and Gunnn, S. 2023)21,22 | County Durham - referrals to service have increased which could lead to increased waiting times. |
| Gascoigne, M. et al. 202323 | Worcestershire - 26% waiting over 18 weeks before reduced to 2%. Lancashire - length of wait before 40 weeks, after 5 weeks. Lancashire - waiting list cleared. |
| Central and North West London NHS Foundation Trust. 202425 | Reduction from average 23.4 weeks to 2.2 weeks from Autism Diagnostic Observation Schedule (ADOS) to feedback; maintained movement of average 2.6 cases from ADOS to feedback. |
| Hannant, P. 202426 | The three cases were all supported holistically in a timely manner at little extra cost. |
| Harding, K. et al. 202427 | All centres waiting times reduced 33% from median of 57 days pre-intervention to 34 days during implementation and to 38 days after implementation, p < 0.01. Mean number of children on waiting list per centre pre implementation (2020) was 67, SD 25.1 and immediately after the implementation period (March 2021) was 22, SD 13.5 (t4 = 3.56, p < 0.01). Reduction observed varied between centres with significant changes at four of the five centres. Two years after the start of this study (July 2022) 2 services continued to operate without a waiting list while other 3 centres experienced some recurrence. Across all 5 centres in total 195 children were waiting, mean 39 per centre (SD 35.8) - 42% lower than at baseline. No impact on employee satisfaction. |
| Hertfordshire Community NHS Trust. 202428 | Waiting times reduced, longest wait before intervention 85 weeks, after 37 weeks. Number waiting for health assessment is reducing. Digital referral form and patient/carer self-booking has reduced Did Not Attend rates. |
| Parr, J. et al. 202431 | Average wait 9 months (paediatrics), 10 months (CAMHS) 2019/20; referrals rose 115% 2015–19; initiatives: school referrals for better triage, combined Autism/ADHD assessment (indirectly). |
| Smith-Young, J. et al. 202532 | Facilitator: professionals listening to concerns. Barrier: financial burden, long public waits leading to private use, lack of specialised professional knowledge (indirectly). |
| Cambridgeshire and Peterborough NHS Foundation Trust. n.d.33 | Reduced average days referral to waiting list (199 to 31); reduced average screening time (33 to 23 mins); reduced average days Qpack received to screened (85 to 6); reduced average days referral to Qpack sent (45 to 0); reduced backlog; more manageable administration; increased clinical time. For reduced clinician time/assessment (237 to 210 mins); reduced days assessment open (39 to 6); reduced multiple appts (6/10 to 3/9); increased same-month completion (3/10 to 7/9). |
The case studies implementing the “balanced system” model of service delivery generally showed promising results in terms of reducing waiting lists. The “balanced” system is a pathway that provides universal basic support to a wide range of children, and targeted support to those with specialist needs, and provides resources and training to schools and GPs in an effort to reduce unnecessary referrals to SALT.23 Waiting times were reduced in Worcestershire from 26% waiting over 18 weeks to 2%, and in Lancashire, the length of wait reduced from 40 weeks to 5 weeks.23 Hertfordshire waiting times reduced, and the longest wait was 37 weeks after the intervention compared with 85 weeks before,28 although funding was used to contract out some assessments to a private company, reducing the number of NHS assessment appointments needed.28
Time target for the whole pathway was only met in 20% of child/adolescent case and children/adolescents and their families had a median wait of 525 days.16 The study also found longer waits for children and adolescents with case complexity and an association between adherence to best-practice quality standards and shorter waits for children/adolescents.16
The Peterborough case study reduced the time children/young people spent on waiting lists from longer than a year to 7–12 weeks, a significant reduction sustained from when the service introduced the single assessment process.14 One of the challenges experienced in introducing the single neurodevelopmental pathway was an increase in referrals which could potentially lead to increased waiting lists.21
Within the UK education system factors that lead to delays were identified and the extra level of assessment added into the pathway enabled timely support for the three cases studied at minimal extra cost.26
Within autism services the objective of reducing waiting times was addressed either directly, (i.e., by each of QI studies), or indirectly, by identifying barriers or facilitators.19,20
Seven of the included studies mapped to the objective of support during waiting times (Table 3).
| Reference | Review objective 2: support during waiting times |
|---|---|
| McLeod, S. et al. 202013 | Children’s speech (percentage of consonants correct) was significantly higher in the therapy group. Post-intervention in the therapy group (Mean rank = 7.40) compared to the face-to-face advice group (Mean rank = −4.72, 95% confidence interval (CI) 4.90–19.34 and p = 0.001), and the website information group (Mean rank = −3.57, 95% CI 4.03–17.90 and p = 0.002). No significant group differences for Children’s intelligibility (Intelligibility in Context Scale, ICS) and children’s language (three Core Language subtests (Sentence Structure, Word Structure and Expressive Vocabulary) from the Clinical Evaluation of Language Fundamentals – Pre-school –Second Edition – Australian Standardised Edition, CELF-P2) and children’s early literacy (Preschool Word and Print Awareness measure, PWPA). Caregiver satisfaction (adapted from the Patient Enablement and Satisfaction Survey, PESS; Australian Primary Health Care Research Institute, Australian National University [APHCRI], and the Australian Medicare Local Alliance [AMLA]) significantly higher in therapy group (Mean rank =6.94) than website information group (Mean rank = −8.13, 95% CI 4.00–26.15 and p = 0.008). Carers’ empowerment (Family Empowerment Scale, FES) non-significant between groups. |
| McGill, N. et al 202115 | Information (website) group versus passive waiting group, no statistically significant differences between groups for children’s speech, intelligibility, language, or literacy. Children’s language in both groups improved a small amount over six months, which authors attributed to natural development. No statistically significant differences for caregivers’ empowerment (Family Empowerment Scale, FES) and satisfaction (Patient Enablement and Satisfaction Survey, PESS). |
| (County Durham Care Partnership n.d. and Wilson, A. and Gunnn, S. 2023)21,22 | County Durham - Brought together information for the local area and there was an emphasis on the availability of support and advice during the whole pathway regardless of diagnosis. One of the challenges they are experiencing is an increase in queries from families and professionals to respond to. |
| Albon, H. et al. 202424 | Parents self-efficacy scores significantly improved after the psychoeducational intervention compared to before (z = −2.52, p = .012), with a large effect size (r = .84). On the adapted BPSES measure for questions one, three, and six there was a statistically significant improvement in the median scores after the intervention. Parents particularly valued meeting the other parents with one group continued to meet after the study. |
| Hertfordshire Community NHS Trust. 202428 | Increased percentage of parents felt confident supporting their child (before intervention 59%, after 98%). |
| Maier, A. et al. 202429 | No significant group differences, Childrens’ communication ANOVA statistical testing (F(2,86) = 1.83, p = .166. In all groups pre- to post, clinically and statistically significant differences in the children’s communication. No significant group differences, (F(2,64) = 1.03, p = .362). In all groups pre- to post, caregivers had statistically significant increases for confidence, behaviour change. |
| Parr, J. et al. 202431 | Support for families during and beyond diagnosis: specialist nurses/early years practitioners increased capacity; most teams unable to meet all NICE guidance. |
Two RCTs, which were companion studies, investigated the provision of advice to families while on the waiting list, either via a purpose-built website or face-to-face. This did not produce significant benefits over passive waiting.13,15 Furthermore, providing a short course of therapy whilst on the waiting list did not produce significant benefits on most measures of children’s language or carers’ empowerment, however there was some benefit over passive waiting on the measures of children’s speech (percentage of consonants correct), and carer satisfaction.13 For children late to talk a low-intensity parent-implemented intervention did not improve their communication or carers’ satisfaction over those not given the intervention.29 A pilot study investigated a psychosocial intervention trialled on nine parents of children awaiting autism or ADHD assessment24 found significant improvement in parental total self-efficacy scores with parents particularly valuing the opportunity to meet other parents. Two autism pathway studies map indirectly to support during waiting times, it was mentioned as a need in one study,20 and reported indirectly by initiatives in another.19
In terms of case studies, in SALT the “balanced” system was reported to increase carers’ confidence.28 In County Durham, the single neurodevelopmental pathway also promotes the provision of information and support once families are referred to the service which has led to the challenge of increased queries from families and professionals.21
Five of the included studies addressed the objective of identifying those who need services directly or indirectly, for more details see Table 4.
| Reference | Review objective 3: identifying those who need services |
|---|---|
| NAIT (Maciver, D. et al 2025 and Rutherford, M. 2020)16,17 | Rutherford - Recommendation for identifying those who need services “behaviour changes, distress, obsessions and compulsions, changes in patterns of eating, sleeping, activity levels or passivity” to be based on professional reports, screening, parent/carer observations, school observations. |
| ELVS (Eadie, P. et al 2022)18 | Children with six or more risk factors had 17 times greater chance (risk ratio 17.11 (95%CI 6.9 to 42.42) p < 0.001) of needing SALT than those with two or fewer risk factors. 5 risk factor RR7.29 (2.70–19.66), p < 0.001; 4 risk factors 5.26 (1.91–14.51), p < 0.001; 3 risk factors RR 3.28 (1.12–9.64), p = 0.03; than two or more risk factors. Authors suggest 4 or more risk factors as indicating need for screening. |
| (County Durham Care Partnership n.d. and Wilson, A. and Gunnn, S. 2023)21,22 | County Durham – potentially better identification of who needs the service as the service is facing the challenge of increased referral numbers. |
| Hannant, P. 202426 | Three cases were all supported holistically in a timely manner at little extra cost. |
| Hertfordshire Community NHS Trust. 202428 | Provision of education leads (liaison between school and SALT service) “significantly reduced number of calls from schools to advice line”. |
The NAIT pathway makes recommendations for how to identify children/young people that could need services.17 Potential concerns to refer for screening were “behaviour changes, distress, obsessions and compulsions, changes in patterns of eating, sleeping, activity levels or passivity”, this would be based on professional reports, screening, parent/carer observations, school observations.
A large prospective community cohort study of risk factors for language development and subsequent need for SALT services conducted in Australia suggested four or more risk factors as indicating a need for screening.18 Risk factors were organised into child risk factors (male sex, low birth weight, low gestures, etc.), family risk factors (non-English speaking in English speaking country/environment, socioeconomic disadvantage, etc.), maternal risk factors (low maternal education, maternal mental health problems), and home learning environment (number of books in the house).18
The case studies of the “balanced system” reported reduced number of calls from schools to advice line,28 and reduced age at time of referral.23
In the case study where an extra level of assessment was investigated the three cases were all supported holistically in a timely manner. The needs of the three cases were met quickly and fully through the whole assessment process instead of focusing on one neurodevelopmental conditional.26 Additionally, the County Durham pathway is experiencing the challenges of increased referral this potentially means that there is better identification of children/young people that need the service.21
Digital tools
A recent NICE guideline on digital assessment for ADHD found that for children and adolescents (ages 6–17) clinical trial data supports incorporating the QbTest into assessments, demonstrating accelerated ADHD diagnosis compared to traditional methods and indicated cost-effectiveness (National Institute for Health and Care Excellence, 2024).
Barriers and facilitators
From the evidence barriers and facilitators were also identified. Common facilitators included the importance of communication with stakeholders, multidisciplinary teams, and multi-agency services, holistic approaches, streamlining services, solutions to staffing problems, and the use of telehealth or digital services. Whilst common barriers included finances, staffing, and lack of specialist knowledge, barriers to the use of telehealth, communication difficulties in inter-agency working, regulation, and barriers to change. Full tables, including details of the studies from which they were extracted, are available at https://orda.shef.ac.uk/collections/_/8488470.
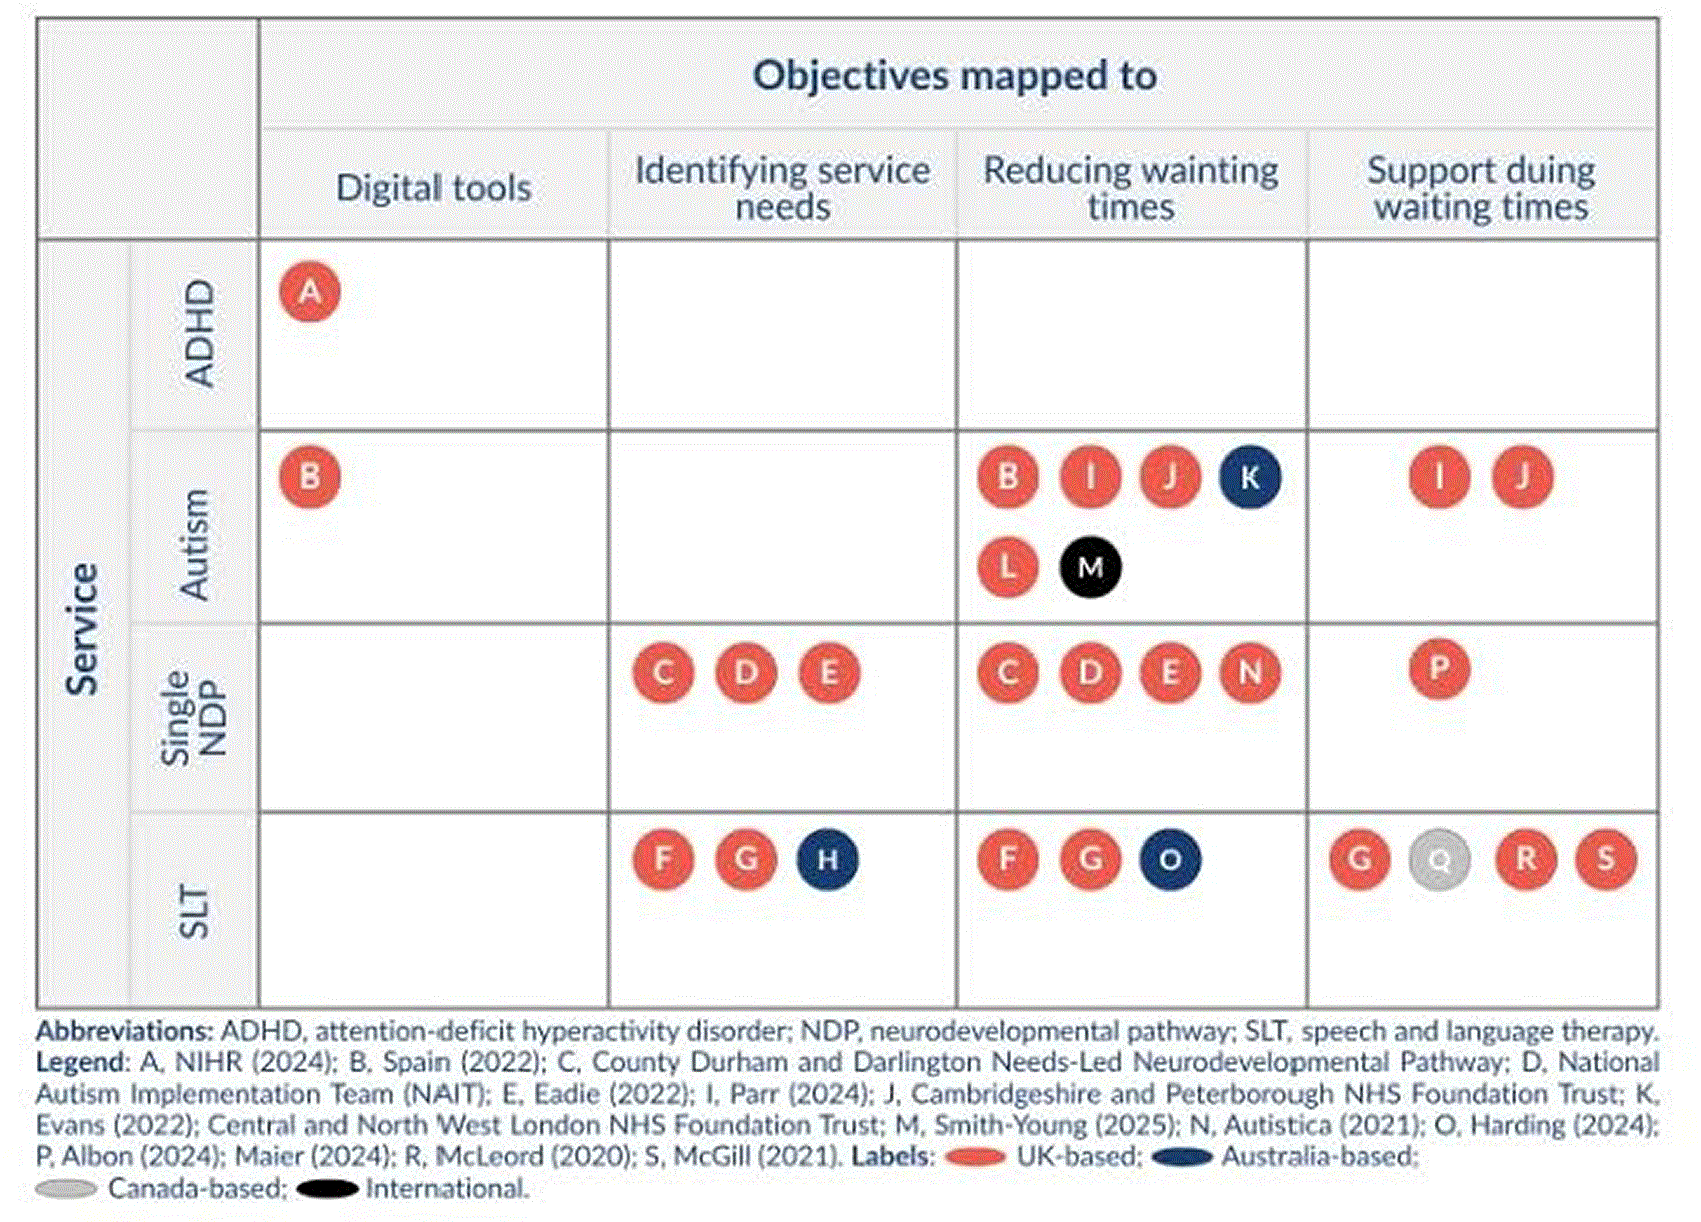
The evidence map created in Excel ( Figure 2 – Evidence Map) shows the distribution and quantity of evidence across services (rows) and across the different objectives (columns) and includes where the study was conducted. The map shows that the majority of the evidence is around reducing waiting times.
In terms of reducing waiting times for SALT, the most promising approaches included the STAT model and the “balanced system”. Both of these approaches showed evidence of significantly reducing waiting times in service implementation studies. Evidence for supporting children and families during waiting periods was less conclusive. Information provision alone, whether via websites or face-to-face advice, showed limited effectiveness compared to treatment, though some benefits were observed for specific outcomes like percentage of consonants correct and parent confidence. For early identification, risk factor screening and school-based approaches showed promise. Children with four or more risk factors were significantly more likely to need SALT services, suggesting a potential screening approach. The integration of SALT services with education through liaison roles appeared to improve early identification, though robust evaluation is needed.
In autism assessment service transformations focused on reducing screening and/or assessment time, reducing overall waiting time and using dashboards to map demand or capacity against redesigned pathways which resulted in reduced waiting time where data was available.
A number of services have developed a single neurodevelopmental pathway, and there has been some impact on waiting times, for example the Peterborough service has seen a sustained reduction in waiting times since the service introduced the single assessment process. Waiting times for children or young people with case complexity were found to be longer, and there could potentially be an initial triage around case complexity. The tension between meeting NICE guidance while offering a holistic needs-led service was highlighted in particular providing support regardless of diagnosis has the potential to lead to increased requests for help which could increase waiting times.
For ADHD assessment in children and adolescents (ages 6–17) there is clinical trial data supporting incorporating the QbTest into assessments, demonstrating accelerated ADHD diagnosis compared to traditional methods and indicating cost-effectiveness.
Barriers and facilitators were summarised across paediatric community services. Common facilitators were multidisciplinary teams, holistic approach and streamlining services. Finances and recruitment and retention were common barriers.
The review demonstrates the need for multi-faceted approaches to managing SALT and neurodevelopmental assessment in community paediatric services, combining service redesign, targeted intervention during waiting periods, and improved screening. Future research should address the identified gaps through longer-term outcome assessments, larger sample sizes, greater demographic diversity, comprehensive cost analyses, and more robust evaluation of service innovations. Services should consider implementing elements of promising models while continuing to evaluate their effectiveness in local contexts. Given the significant impact of delayed access to neurodevelopmental assessment and SALT services on children’s development and family wellbeing, there is a clear imperative to continue developing and evaluating innovative approaches to service delivery that can both reduce waiting times and provide meaningful support during inevitable waiting periods.
This mapping review was primarily limited by its narrow timeframe (2020–2025) which may have excluded relevant earlier evidence. The focus on UK-based studies initially constrained the evidence base, though this was appropriately expanded to include studies from Australia and Canada for SALT. Whilst limiting the evidence base this did ensure applicability for NHS England. Our team mitigated against a common limitation of mapping reviews, a heavy reliance on published sources, by conducting extensive searches of unpublished sources and sites that feature innovations, although the yield remained low.
The review did not include a formal quality assessment of the included studies, an approach appropriate for a mapping review but which limits the ability to make strong recommendations based on the quality of evidence.
The evidence base for community paediatric services has several key limitations. Most of the included studies had small sample sizes. There were only two RCTs within the evidence base and they were also small including between 42–110 participants, limiting statistical power and generalisability. There was limited demographic information, with minimal reporting on ethnicity, socioeconomic status, or other potential health inequalities across most studies meaning that it is not possible to comment on diversity and inclusion. Additionally, cost information was notably absent, with no studies providing comprehensive cost data for interventions or service redesigns. Long-term outcomes were rarely reported, with most studies focusing on immediate or short-term impacts. Many service innovations were reported in case studies without robust evaluation methodologies, making it difficult to determine their effectiveness and transferability. Additionally, we found limited evidence on digital approaches to service delivery, despite growing interest in this area.
The included studies provided limited reporting of participant ethnicity, with none of the included studies reporting socioeconomic status, making it difficult to comment on diversity and inclusion. Detailed information about the staff involved in the intervention was available in only a few studies similarly the outcome of costs.
This mapping review identified diverse approaches to reduce waiting times, support children and families during waiting periods, and improve early identification of needs for speech and language therapy services and neurodevelopmental assessment in a community paediatric service. The findings suggest that multi-faceted approaches combining service redesign, targeted intervention during waiting periods, and improved screening could be the most promising to address paediatric community service challenges. Future research should prioritise longer-term outcome assessment, larger sample sizes, greater demographic diversity, comprehensive cost analyses, and more robust evaluation of service innovations. The evidence map shows that the majority of the evidence is around reducing waiting times and identifying those who need services. There is inconclusive evidence around support during waiting times for SALT and limited evidence around support during waiting times for neurodevelopmental assessment. Increasing waiting times means that providing support during waiting times is becoming more important. As services start to offer support regardless of diagnosis hopefully robust evaluation will follow.
Anna Cantrell: Conceptualization, Data Curation, Formal Analysis, Funding Acquisition, Methodology, Writing – Original Draft Preparation, Writing – Review & Editing; Lukasz Lagojda: Conceptualization, Data Curation, Formal Analysis, Funding Acquisition, Methodology, Writing – Original Draft Preparation, Writing – Review & Editing; Emily Pulsford: Conceptualization, Formal Analysis, Investigation, Writing – Review & Editing; Emma Simpson: Conceptualization, Data Curation, Formal Analysis, Funding Acquisition, Methodology, Writing – Original Draft Preparation, Writing – Review & Editing. All other aspects checked and are correct.
Provide sufficient details of any financial or non-financial competing interests to enable users to assess whether your comments might lead a reasonable person to question your impartiality. Consider the following examples, but note that this is not an exhaustive list:
Sign up for content alerts and receive a weekly or monthly email with all newly published articles
Register with NIHR Open Research
Already registered? Sign in
If you are a previous or current NIHR award holder, sign up for information about developments, publishing and publications from NIHR Open Research.
We'll keep you updated on any major new updates to NIHR Open Research
The email address should be the one you originally registered with F1000.
You registered with F1000 via Google, so we cannot reset your password.
To sign in, please click here.
If you still need help with your Google account password, please click here.
You registered with F1000 via Facebook, so we cannot reset your password.
To sign in, please click here.
If you still need help with your Facebook account password, please click here.
If your email address is registered with us, we will email you instructions to reset your password.
If you think you should have received this email but it has not arrived, please check your spam filters and/or contact for further assistance.

Comments on this article Comments (0)